Servicios Personalizados
Revista

Articulo
 Inglés (pdf)
 Articulo en XML
 Referencias del artículo

 Traducción automática
 Enviar articulo por email
Indicadores
Links relacionados
-
 Citado por Google
-
 Similares en Google
Compartir

 Permalink

South African Journal of Child Health
versión On-line ISSN 1999-7671versión impresa ISSN 1994-3032
S. Afr. j. child health vol.19 no.3 Pretoria sep. 2025
https://doi.org/10.7196/SAJCH.2025.v19i3.1518
ARTICLE
Antimicrobial prescribing practices for children hospitalised with respiratory tract illnesses at a tertiary public sector hospital in South Africa
S MagrathI; N KhumaloII; T MsibiIII; L NkosiIV; S NkosiV; Z WaggieVI; Z DangorVII, VIII; M SharlandIX; S A MadhiX, XI; D P MooreXII, XIII
IMSc; School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
IISchool of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
IIIBA Hons; School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
IVEN; School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
VEN, MSc (Wits);School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
VIMB ChB, FCPaed (SA); Department of Paediatrics and Child Health, Chris Hani Baragwanath Academic Hospital and University of the Witwatersrand, Johannesburg, South Africa
VIIMB BCh, PhD, Cert Pulm (SA); Department of Paediatrics and Child Health, Chris Hani Baragwanath Academic Hospital and University of the Witwatersrand, Johannesburg, South Africa
VIIIMB BCh, PhD, Cert Pulm (SA); South African Medical Research Council Vaccines and Infectious Diseases Analytics Research Unit (Wits-VIDA), University of the Witwatersrand, Johannesburg, South Africa
IXMD; St George's University of London, London, United Kingdom
XMB BCh, PhD; South African Medical Research Council Vaccines and Infectious Diseases Analytics Research Unit (Wits-VIDA), University of the Witwatersrand, Johannesburg, South Africa
XIMB BCh, PhD; Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
XIIMB BCh, PhD School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa
XIIIMB BCh, PhD Department of Paediatrics and Child Health, Chris Hani Baragwanath Academic Hospital and University of the Witwatersrand, Johannesburg, South Africa
ABSTRACT
BACKGROUND. Antimicrobial prescribing practices for children hospitalised with lower respiratory tract infections (LRTIs) are infrequently reported, particularly in developing countries.
OBJECTIVES. We evaluated the antimicrobials prescribed to children with severe respiratory illness hospitalised at Chris Hani Baragwanath Academic Hospital (CHBAH) in Johannesburg, South Africa, from 22 July until 22 September 2021.
METHODS. Children aged 1 month to 14 years who were hospitalised with severe acute respiratory illness were enrolled. We assessed frequency of antibiotic usage, admission diagnoses and 28-day outcomes.
RESULTS. A total of 183 children were screened and 85 (46.4%) were enrolled. Most of the enrolled children (n/N=75/85; 88.2%) received antibiotic therapy. The most common diagnoses were bronchiolitis (n/N=30/85; 35.3%), LRTI (n/N=21/85; 24.7%), and pneumonia (n/N=18/85; 21.2%). Twenty-five (83.3%) of the children with bronchiolitis were treated with antibiotic therapy. Of the 122 antibiotics prescribed, 109 (89.3%) were classified in the WHO AWaRe groups of antimicrobials, and 95 (77.9%) were 'Access' antibiotics. Co-amoxiclav, amoxicillin and ampicillin were the most commonly prescribed antimicrobials. The median length of hospitalisation in those who survived to discharge was 3 (1 - 57) days. Three children died, two in-hospital and one post discharge.
CONCLUSION. Antimicrobials are commonly prescribed to children with severe respiratory illness hospitalised at CHBAH. Children with bronchiolitis were commonly treated with antimicrobials and should be targeted as a major focus group for optimisation of antimicrobial stewardship practice.
Keywords: child; respiratory infection; antibiotics; bronchiolitis; antimicrobial stewardship.
Lower respiratory tract infections (LRTIs) are a leading cause of death in children less than five years of age globally, although the burden of disease and mortality is declining steadily due to increasing access to vaccines, improvements in the care of immunocompromised children, and increasing access to healthcare facilities.[1] LRTI is a blanket term, which includes a spectrum of infectious syndromes of the lung, spanning from bronchiolitis (which is typically caused by respiratory viruses) and bronchopneumonia, to pneumonia associated with consolidation of the alveolar spaces (which may be caused by respiratory viruses, bacteria, fungi, or a combination of infecting organisms).
In the era before access to the polysaccharide-protein vaccines that target Haemophilus influenzae type b and Streptococcus pneumoniae, these two pathogens were responsible for over 50% of all childhood pneumonia episodes.[4] With increasing access to highly effective vaccines that reduce the risk of pneumonia caused by these bacteria, respiratory viruses have come into prominence as leading causes of paediatric pneumonia requiring hospitalisation. In the Pneumonia Etiology Research for Child Health (PERCH) Study, respiratory syncytial virus (RSV) was the leading cause of radiologically confirmed pneumonia in HIV-uninfected children less than 5 years of age, and respiratory viruses generally caused 61.4% (95% credible interval 57.3 - 65.6%) pneumonia episodes.[5]
The World Health Organization (WHO) established a classification system of pneumonia in 2005,[2] which was updated in 2013[3] and promotes the use of a highly sensitive but nonspecific case definition of childhood pneumonia. WHO guidelines for treatment of severe childhood pneumonia recommends use of ampicillin (or penicillin) and gentamicin administered intravenously for five days,[24] as there is no established clinical or biochemical marker to differentiate bacterial from viral infection. Over-reliance on antimicrobial therapy drives antimicrobial resistance (AMR), therefore it is important to rationalise antimicrobial prescribing in children hospitalised with pneumonia. Paediatric pneumonia guidelines currently recommend antibiotic therapy as part of the management of children hospitalised with pneumonia, although many pneumonia episodes may be caused by viruses.[6]
We evaluated the antibiotic prescribing practices of clinicians treating children hospitalised with respiratory infections at Chris Hani Baragwanath Academic Hospital (CHBAH), a public sector facility in Johannesburg, South Africa (SA).
Methods
This study was a site-specific sub-study of the PediCAP Trial (https://penta-id.org/severe-infections-and-antimicrobial-resistance/pedicap/), a trial undertaken in SA, Mozambique, Uganda, Zimbabwe and Zambia that investigated the efficacy of oral step-down antibiotic treatment for children aged two months to six years hospitalised with severe pneumonia in preventing death or re-hospitalisation within 28 days of randomisation. PediCAP inclusion criteria were a point-of-care C-reactive protein (CRP) level >10 mg/L and an admission diagnosis of severe pneumonia requiring at least 24 hours of intravenous antibiotic therapy (ampicillin, ampicillin and gentamicin, ceftriaxone or cefotaxime). Treatment arms in PediCAP were assigned through a centralised randomisation process, with participants receiving either five days of intravenous antibiotic therapy, or step-down to dispersible amoxicillin or co-amoxiclav tablets for 4 to 8 days of treatment. In PediCAP, study participants were followed for a period of four weeks post randomisation to evaluate the primary outcome of readmission or death.
Children admitted to the general paediatric wards at CHBAH, from 22 July to 22 September 2021 were enrolled into this sub-study if deemed ineligible for PediCAP enrolment. The rationale for including children that were ineligible for inclusion in the PediCAP trial was so that we could evaluate the regular prescribing practices of clinicians when treating children hospitalised with respiratory tract infections. Children with an admission diagnosis predominantly due to asthma were not considered for enrolment, unless they were on antimicrobial therapy.
Participant clinical and demographic details, including antibiotic regimens, were entered into case report forms and captured electronically for data cleaning and analysis. Reasons for not being enrolled into PediCAP, demographic and clinical data, admission and discharge diagnoses, outcome and length of hospitalisation were also recorded. Antimicrobial therapy used during the hospitalisation, and outcome at 28 days after enrolment were evaluated through inpatient follow-up assessments and telephonic follow-up interviews post discharge.
Conventional descriptive statistical methods were used to analyse the data. Additionally, we compared the characteristics of children hospitalised with a diagnosis of bronchiolitis and those of children with other LRTI diagnoses to appraise the differences in clinical characteristics between the groups. Duration of antimicrobial therapy for those discharged home on anti-tuberculosis therapy was censored on 15 November 2021 for the calculation of total antimicrobial administration for the study participants, combined. This cut-off date was arbitrarily chosen to accommodate prolonged therapy in children discharged on anti-tuberculosis therapy. All analyses were done using R version 4.2.2 (R Core Team).[8]
Written informed consent was obtained from caregivers, and assent was obtained from children older than 7 years of age. The Human Research Ethics Committee (Medical) of the University of the Witwatersrand Faculty of Health Sciences approved the study (ref. no. M210606).
Results
In the 2-month study period, there were 934 general paediatric admissions to CHBAH, of which 247 (26.4%) were admitted with respiratory illness. Of these, 183 (74.1%) were screened for inclusion, of which 85 (46.4%) were enrolled. The most common reasons for non-enrolment (n=98) included inability to contact caregivers (n=34; 34.7%), refusal of consent (n=16; 16.3%), and screening failure (n=12; 12.2%). Screening failure occurred when the child was eligible for inclusion but not enrolled erroneously. Among the enrolled children, reasons for non-enrolment into the PediCAP Trial included being age-ineligible (n=11), having low CRP levels (n=17), not having been started on antibiotic treatment for their respiratory illness (n=9) and clinician antibiotic choice (n=48).
Characteristics of the study participants
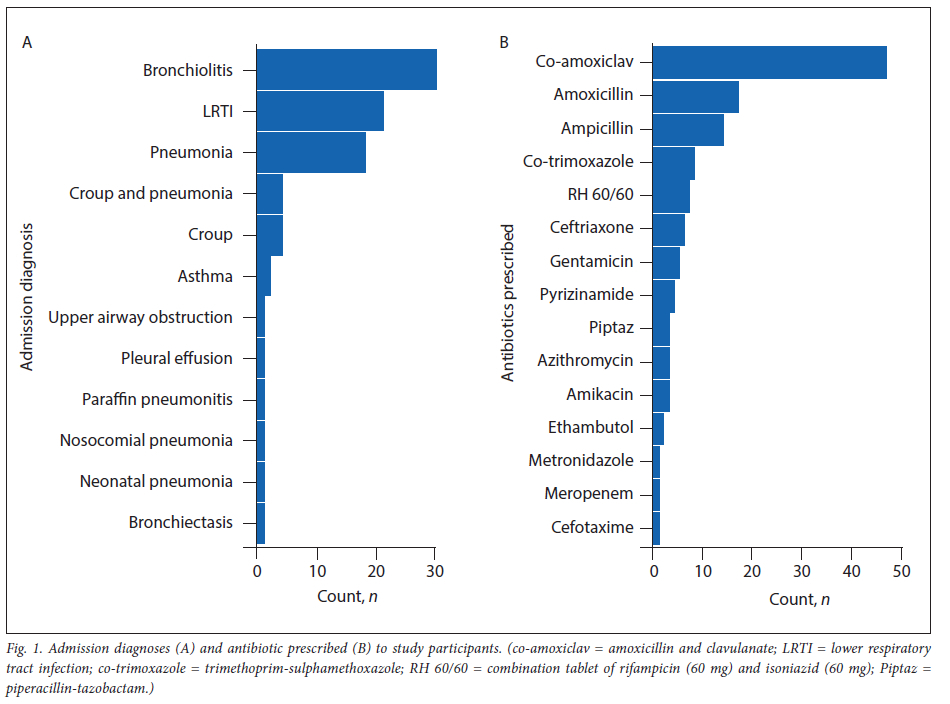
The most common diagnoses included bronchiolitis, LRTI and pneumonia, which were diagnosed in 69 (81.2%) of the participants (Fig. 1a). There were 67 (78.8%) HIV-negative children, 15 (17.6%) with undetermined HIV infection status and three (3.5%) HIV-positive children. The three HIV-positive children were admitted with diagnoses of pneumonia (n=2) and bronchiolitis (n=1). One of the HIV-positive patients (a 10.4-year-old male) had an undetectable HIV viral load and a CD4 cell count of 128 cells/μL on a dolutegravir-based ART regimen. The other two HIV-positive children (aged 3.0 and 13.3 months, respectively) were ART-na'ive, and presented with respiratory infections as part of the sentinel HIV diagnosis.
Antimicrobial therapy prescribed to study participants
Of the 76 (89.4%) children that received any antimicrobial therapy (inclusive of antivirals, antifungals and antibiotics), 75 (98.7%) received antibiotic therapy. Of the children prescribed antibiotic therapy, 40 (53.3%) received intravenous therapy only, 19 (25.3%) received oral therapy only, and 16 (21.3%) received intravenous and oral antibiotic therapy. A diagnosis of pneumonia or LRTI (n/ N=39/75, 52.0%) was significantly more common than in those that received antibiotic therapy, compared with the group of children that did not receive antibiotic therapy (n/N=0/10); p=0.002. Conversely, a diagnosis of croup was significantly associated with a clinician decision not to use antimicrobial therapy (n/N=3/10; (30.0%) v. n/N=1/75 (1.3%); p=0.005).
Antibiotic agents comprised 122 (89.7%) of all 136 antimicrobials prescribed to study participants, 6 (4.4%) were antivirals and 6 (4.4%) were antifungals. The three most commonly prescribed antibiotics were co-amoxiclav, amoxicillin and ampicillin, which together comprised 78 (63.9%) of all 122 prescribed antibiotics (Fig. 1b). Of the antibiotics prescribed, 109 (89.3%) were classified in the WHO AWaRe group of antimicrobials, and most (n/N=95/109; 77.9%) were 'Access' antibiotics (Fig. 1b). The median duration of antibiotic therapy was 6.0 days (interquartile range (IQR) 3.0 - 9.3 days), and 47 (62.7%) received more than 5 days of therapy. Children with a longer course of treatment were significantly underweight for their age compared with those who received less than 5 days of treatment (-1.31 (IQR -2.68 - -0.16) v. -0.77 (IQR -1.14 - -0.10); p=0.046).
Antibiotics prescribed to children with bronchiolitis
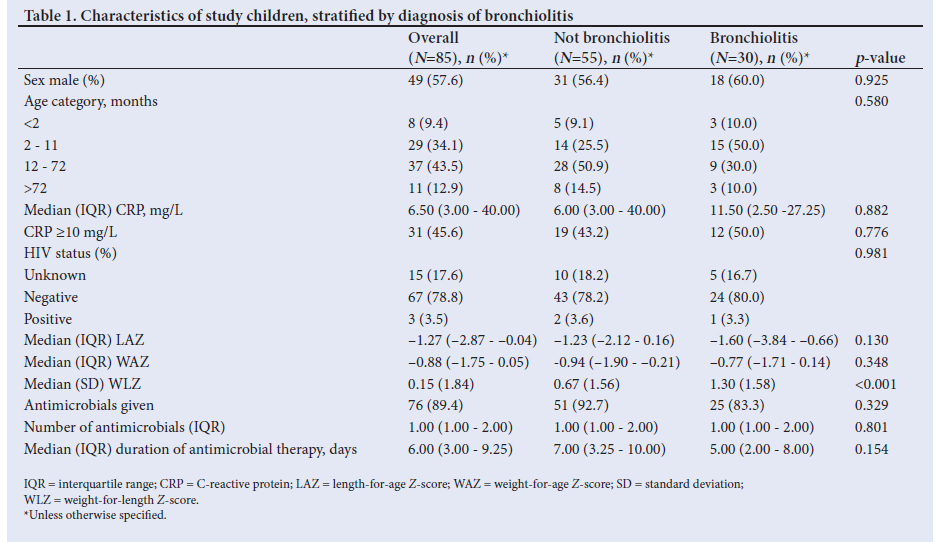
Twenty-five (83.3%) ofthe 30 children with an admission diagnosis of bronchiolitis received antimicrobial therapy (Table 1). Children with an admission diagnosis of bronchiolitis were significantly younger and had significantly greater median weight-for-length Z-scores than those without bronchiolitis (Table 1). Median CRP levels were similar in children that were diagnosed with bronchiolitis and those without bronchiolitis (11.5 v. 6.0 mg/L; p=0.882) (Table 1). The median CRP value (n=22) in children diagnosed with bronchiolitis that were treated with antibiotics was 15.0 mg/L (range 1.0 - 151.0 mg/L) - 6 (27.3%) had a CRP >40 mg/L.
CRP test results and impact on antibiotic duration
Of the 68 children with available CRP results, 37 (54.4%) had a formal CRP level of <10 mg/L. Children with CRP levels >10 mg/L were significantly older (24.3 months (IQR 9.9 - 75.6) v. 11.6 months (IQR 3.0 - 31.7)) compared with those with lower CRP levels (p=0.011). Median length of antimicrobial therapy was similar regardless of the admission CRP level (7.0 days (IQR 4.5 - 7.5) v. 6.0 days (IQR 3.0 - 9.0) in children with elevated CRP and those with CRP <10 mg/L, respectively; p=0.838).
Microbiology results
Two children had bacteraemic pneumonia attributable to clinically significant bacteria: an 11-year-old male with methicillin-susceptible Staphylococcus aureus, and a 3.0-month-old HIV-infected male with extended spectrum β-lactamase producing Klebsiella pneumoniae bacteraemia. Both children died during their hospitalisation. The blood culture contamination rate was 10.6% (n/N=9/85). Seven children commenced anti-tuberculosis therapy during their hospitalisation, one (14.3%) of which had microbiologically confirmed tuberculosis.
Outcomes
Eighty-two (96.5%) children were discharged home, one (1.2%) was transferred out but subsequently died, and two (2.4%) died during their admission. At 28 days post discharge among the 83 children who survived to hospital discharge, 68 (81.9%) were alive and well, 1 (1.2%) was alive and ill, 2 (2.4%) were still admitted to hospital, 4 (4.8%) were readmitted and 7 (8.3%) were not traceable via telephonic follow-up. One child (1.2%), a 2-year-old male with a diagnosis of tuberculosis, died post discharge. The overall case-fatality rate in children with known outcomes at 28 days post discharge was 3.8% (n/N=3/78). Case fatality was higher in HIV-infected (n/N=1/3; 33.3%) compared with HIV-uninfected children (n/N=1/60; 1.7%).
Discussion
In this descriptive study of 85 children that were hospitalised with severe respiratory distress and a clinician-diagnosed acute respiratory infection, 75 (88.2%) were administered antibiotic therapy by treating clinicians. Furthermore, of children with an admission diagnosis of bronchiolitis, 83.3% were prescribed antibiotic therapy. Co-amoxiclav, ampicillin and amoxicillin were the most commonly prescribed antibiotics, in keeping with SA paediatric pneumonia guideline recommendations,[9] and with findings from studies conducted elsewhere, which evaluated treatment administered to children hospitalised with LRTI.[12,13,14]
The high proportion of children treated with antibiotics in this study is comparable with findings from studies in Jordan,[12] Vietnam[13] and the USA,[11] where antibiotic prescribing for paediatric acute severe respiratory hospitalisations ranged from 78.4% to 98%. Lower rates of antibiotic prescribing (27 - 39%) are described for children with severe respiratory illness that were treated in Spain and Bangladesh.[14,15] Heterogeneity of antibiotic prescribing between studies could be due to differences in patient characteristics and different guidelines for antimicrobial use.
Antibiotics accounted for 90.4% of the antimicrobials administered to patients in the present study. This is similar to findings in a point-prevalence survey (PPS) in Ghana, where 91.1% of the antimicrobials used were antibiotics.[16] An antimicrobial use PPS of children in six hospitals in India found that 90.8% of antimicrobials given to the children were antibiotics.[17] The majority (89.3%) of the antibiotics prescribed in our study were included in the WHO AWaRe classification, and 77.9% were 'Access' antibiotics. None of the patients were treated with 'Reserve' antibiotics. These are positive findings, as the WHO recommends that 60% or more of antimicrobials prescribed should be from the 'Access' group and those in the 'Reserve' group should be used as little as possible, as a last resort treatment option.[18] A diagnosis of croup was associated with an attending clinician's decision to not treat with antibiotics, consistent with studies which show that in croup of any severity, antibiotics do not improve symptoms.[19]
A lower CRP suggests that the infection is more likely viral rather than bacterial.[20,21] Point-of-care CRP testing has been shown to limit antimicrobial prescription (by clinicians) to children with suspected LRTI in high-income settings.[22,23] Point-of-care testing is feasible in sub-Saharan African healthcare settings with rudimentary laboratory facilities and may positively affect clinical management of patients.[24] However, it is important to consider that in sub-Saharan Africa, there is an increased risk of mixed bacterial-viral infections in the context of the malnourished, HIV-exposed or HIV-infected child, as well as children with other co-morbidities that may warrant antimicrobial use if hospitalised.
Most acute respiratory infections, including bronchiolitis, are caused by self-limiting viral infections and therefore do not require treatment with antibiotics. Many of these infections are treated with antibiotics, with negative impacts on antibiotic stewardship.[25] In the USA and SA, guidelines caution against treatment of children with bronchiolitis using antibiotics unless there is evidence of concomitant bacterial co-infection.[26,27] Available evidence suggests that antibiotics should not be prescribed in uncomplicated bronchiolitis, except in children with more severe disease, those needing intensive care unit admission, or those with risk factors for severe disease.[27]
Study strengths and limitations
Funding constraints and limited availability of the principal investigator to prospectively enrol all potentially eligible participants contributed to the inclusion of only a small proportion (n/N=85/247; 34.4%) of all children hospitalised with LRTI during the 2-month study period. However, we highlight heavy reliance (by clinicians) on antibiotic therapy prescription in the management of children hospitalised with LRTI in a SA public sector academic hospital.
Conclusion
The finding of possible over-reliance on antimicrobial therapy in children with an admission diagnosis of respiratory illness is concerning, particularly in the context of the well-described shift in aetiology of paediatric LRTIs from bacterial to viral organisms.[5-The high prevalence of antimicrobial prescribing for children with an admission diagnosis of bronchiolitis (n/N=25/30; 83.3%) suggests that clinicians are averse to withholding antibiotic therapy in these children. Future studies evaluating the utility of point-of-care CRP testing to assist clinicians in their approach to antimicrobial prescribing for children requiring hospitalisation for bronchiolitis may be helpful in guiding clinicians in their use of antimicrobial therapy.
Declaration. The study was conducted in partial fulfilment of the requirements of an MSc at the Faculty of Health Sciences, University of the Witwatersrand, which was awarded to SM in 2022.
Acknowledgements. The authors wish to thank the study participants and their parents for their contribution to this work. Furthermore, they wish to acknowledge the members of staff at the Department of Paediatrics and Child Health at Chris Hani Baragwanath Academic Hospital for facilitating the in-hospital management of the study participants and permitting the research team to interact with and recruit the study participants. DPM was in part funded through a grant awarded by the Carnegie Foundation of New York during his participation in this study.
Author contributions. SM and DPM conceived the study; MS, DPM and SAM coordinated the PediCAP Trial at the Chris Hani Baragwanath Academic Hospital site; DPM, ZD and ZW were involved in screening for eligibility into the PediCAP Trial and assisted SM in identifying study participants that were eligible for enrolment into the current study; NK, TM, LN and SN assisted with screening for eligibility into PediCAP, informing SM of study participants that were eligible for this study, and clinical data collection and curation; all authors critically appraised the contents of the manuscript.
Funding. None.
Conflicts of interest. MS Chaired the 2023 WHO Expert Committee on Selection and Use of Essential Medicines.
References
1. GBD 2016 Lower Respiratory Infections Collaborators. Estimates of the global, regional, and national morbidity, mortality, and aetiologies of lower respiratory infections in 195 countries, 1990 - 2016: A systematic analysis for the Global Burden of Disease Study 2016. Lancet Infect Dis 2018;18(11):1191-1210. [ Links ]
2. World Health Organization. Cough or difficult breathing. In: World Health Organization, ed. Pocket Book of Hospital Care for Children: Guidelines for the Management of Common Illnesses with Limited Resources. Geneva: WHO, 2005:72-78.https://apps.who.int/iris/bitstream/10665/ 81170/1/9789241548373_eng.pdf (accessed 11 November 2021). [ Links ]
3. World Health Organization. Cough or difficult breathing. In: World Health Organization, ed. Pocket Book of Hospital Care for Children: Guidelines for the Management of Common Illnesses with Limited Resources. Geneva: WHO, 2005:75-124. https://apps.who.int/iris/bitstream/10665/81170/1/9789241548373_eng.pdf (accessed 11 November 2021). [ Links ]
4. Scott JA, English M. What are the implications for childhood pneumonia of successfully introducing Hib and pneumococcal vaccines in developing countries? PLoS Med 2008;5(4):e86. https://doi.org/10.1371/journal.pmed.0050086. [ Links ]
5. Pneumonia Etiology Research for Child Health (PERCH) Study Group 2019. Causes of severe pneumonia requiring hospital admission in children without HIV infection from Africa and Asia: The PERCH multi-country case-control study. Lancet 2019;394(10200):757-779. https://doi.org/10.1016/s0140-6736(19)30721-4 [ Links ]
6. Bradley JS, Byington CL, Shah SS, et al. The management of community- acquired pneumonia in infants and children older than 3 months of age: Clinical practice guidelines by the Pediatric Infectious Diseases Society and the Infectious Diseases Society of America. Clin Infect Dis 2011;53(7):617-630. https://doi.org/10.1093/cid/cir625 [ Links ]
7. Harris M, Clark J, Coote N, et al. British Thoracic Society guidelines for the management of community acquired pneumonia in children: Update 2011. Thorax 2011;66(Suppl 2):ii1-23. https://doi.org/10.1136/thoraxjnl-2011-200598 [ Links ]
8. R Core Team, 2021. A Language and Environment for Statistical Computing. R Foundation for Statistical Computing. https://www.R-project.org/ (accessed 3 July 2025). [ Links ]
9. Zar HJ, Moore DP, Andronikou S, et al. Diagnosis and management of community-acquired pneumonia in children: South African Thoracic Society guidelines. Afr J Thorac Crit Care Med 2020;26(3):e104. https://doi.org/10.7196/AJTCCM.2020.v26i3.104 [ Links ]
10. Fondazione Penta Onlus. PediCAP. 2019. https://projectpedicap.org/ (accessed 27 June 2022). [ Links ]
11. Nyquist A, Gonzales R, Steiner J, Sande M. Antibiotic prescribing for children with colds, upper respiratory tract infections, and bronchitis. JAMA 1998;279(11):875-877. https://doi.org/10.1001/jama.279.11.875 [ Links ]
12. Ababneh M, Al-Azzam S, Ababneh R, Rababa'h A, Al Demour S. Antibiotic prescribing for acute respiratory infections in children in Jordan. Int Health 2017;9(2):124-130. https://doi.org/10.1093/inthealth/ihx003 [ Links ]
13. Nguyen P, Tran H, Fitzgerald D, Graham S, Marais B. Antibiotic use in children hospitalised with pneumonia in Central Vietnam. Arch Dis Child 2020;105(8):713-719. https://doi.org/10.1136/archdischild-2019-317733 [ Links ]
14. Malo S, Bjerrum L, Feja C, Lallana M, Poncel A, Rabanaque M. Antibiotic prescribing in acute respiratory tract infections in general practice. An Pediatr 2015; 82(6):412-416. https://doi.org/10.1016/j.anpedi.2014.07.016 [ Links ]
15. Hassan Z, Mojur BM, Chowdhury F, et al. Antibiotic use for acute respiratory infections among under-5 children in Bangladesh: A population-based survey. BMJ Glob Health 2021;6(4):e004010. https://doi.org/10.1136/bmjgh-2020-004010 [ Links ]
16. Labi A, Obeng-Nkrumah N, Dayie N, et al. Antimicrobial use in hospitalised patients: A multicentre point prevalence study across seven hospitals in Ghana. JAC Antimicrob Resist 2021;(3):dlab087. https://doi.org/10.1093/jacamr/dlab087 [ Links ]
17. Gandra S, Singh S, Jinka D, et al. Point prevalence surveys of antimicrobial use among hospitalised children in six hospitals in India in 2016. Antibiotics 2017;6(3):19. https://doi.org/10.3390/antibiotics6030019 [ Links ]
18. Mugada V, Mahato V, Andhavaram D, Vajhala S. Evaluation of prescribing patterns of antibiotics using selected indicators for antimicrobial use in hospitals and the Access, Watch and Reserve (AWaRe) classification by the World Health Organization. Turk J Pharm Sci 2021;18(3):282-288. 10.4274/tjps.galenos.2020.11456 [ Links ]
19. Johnson, D. Croup. BMJ Clin Evid 2009:0321. [ Links ]
20. Martinez-Gonzalez N, Keizer E, Plate A, et al. Point-of-care C-reactive protein testing to reduce antibiotic prescribing for respiratory tract infections in primary care: Systematic review and meta-analysis of randomised controlled trials. Antibiotics 2020;9(9):610. https://doi.org/10.3390/antibiotics9090610 [ Links ]
21. Cals J, Chappin F, Hopstaken R, et al. C-reactive protein point-of-care testing for lower respiratory infections: A qualitative evaluation of experiences by GPs. Fam Prac 201027(2):212-218. https://doi.org/10.1093/fampra/cmp088 [ Links ]
22. Bernstein D, Coster D, Berliner S, et al. C-reactive protein discriminates between acute viral and bacterial infections in patients who present with relatively low CRP concentrations. BMC Infect Dis 2021;21:2110. https://doi.org/10.1186/s12879-021-06878-y [ Links ]
23. Escafadal C, Incardona S, Fernandez-Carballo B, Dittrich S. The good and the bad: Using C-reactive protein to distinguish bacterial from non-bacterial infection among febrile patients in low-resource settings. BMJ Glob Health 2020;5(5):e002396. https://doi.org/10.1136/bmjgh-2020-002396 [ Links ]
24. Ciccone E, Kabugho L, Baguma E, et al. Rapid diagnostic tests to guide case management of and improve antibiotic stewardship for paediatric acute respiratory illnesses in resource-constrained settings: A prospective cohort study in southwestern Uganda. Microbiol Spectr 2021;9(3):e0169421. https://doi.org/10.1128/Spectrum.01694-21 [ Links ]
25. World Health Organization. Revised WHO classification and treatment of childhood pneumonia at health facilities: Evidence summaries Geneva: World Health Organization, 2014. https://iris.who.int/bitstream/handle/10665/137319/9789241507813_eng.pdf (accessed 11 Novemwber 2021). [ Links ]
26. Papenburg J, Fontela P, Freitas R, Burstein B. Inappropriate antibiotic prescribing for acute bronchiolitis in US emergency departments, 2007 - 2015. Pediatric Infect Dis Soc 2019;8(6):567-570. https://doi.org/10.1093/jpids/piy131 [ Links ]
27. Green R, Zar H, Jeena P, Madhi S, Lewis H. South African guideline for the diagnosis, management and prevention of acute viral bronchiolitis in children. S Afr Med J 2010;100(5):320-325 [ Links ]
 Correspondence:
D P Moore
david.moore@wits.ac.za
Received 6 October 2023
Accepted 7 May 2025